
Physical Therapy Guide to Congenital Heart Defects
Congenital heart defects are the most common type of condition present at birth. They occur in about 1% of births each year. CHDs affect the normal structure of the heart and the way it works. Young children and teens with CHD often need physical therapy due to problems meeting motor (movement) milestones, decreased tolerance for play and activity, or to address the effects of surgery.
Physical therapists are movement experts who use the latest evidence to design treatment plans for each person’s needs and goals. They improve quality of life through hands-on care, patient education, and prescribed movement. You can contact a physical therapist directly for an evaluation. To find a physical therapist in your area, visit Find a PT.
What Is a Congenital Heart Defect?
A congenital heart defect is a problem with the structure of the heart that is present at birth. Some heart defects are mild and may need little or no treatment. Others are more complex and require surgery or long‑term medical care. Even children with the same diagnosis can have very different symptoms, energy levels, and activity needs.
How the Heart Normally Works
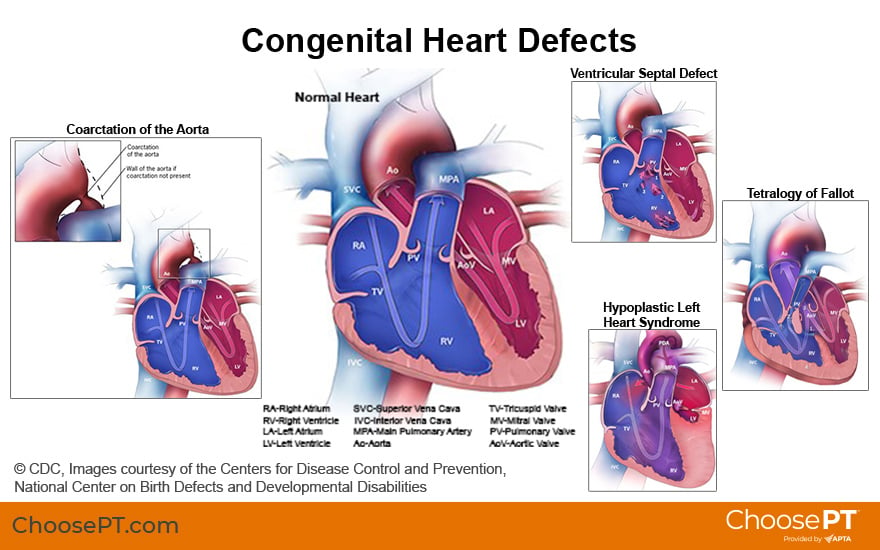
To understand CHDs, it may help to first review normal blood flow through the heart. The heart has four hollow chambers. They are the:
- Right atrium.
- Right ventricle.
- Left atrium.
- Left ventricle.
Heart function and disease are generally described in terms of the heart's right and left sides.
In a healthy heart, blood travels from the right atrium to the right ventricle, and then is pumped into the lungs. In the lungs, blood picks up oxygen and becomes oxygenated. It then travels back to the left side of the heart and enters it. The oxygen-rich blood travels through the left atrium and left ventricle. It is then pumped to the rest of the body through a large blood vessel (the aorta). After delivering oxygen throughout the body, blood returns to the right side of the heart to repeat this process.
With CHD, blood flow through the heart may not follow its normal path, which can make the heart work harder than usual. The path may be altered within the heart's chambers or at the vessels (tubes) that carry blood to and from the heart.
There are two categories of CHD:
Acyanotic
Acyanotic heart defects typically do not impact oxygen levels delivered throughout a child’s system/body.
With an acyanotic defect, blood travels normally from the right side of the heart to the lungs. However, when it returns to the left side of the heart, some blood continues to the rest of the body as normal, while some also travels back into the right side of the heart without first going to the body. This is also known as “left to right shunting.” In an acyanotic defect, the child generally does not have a bluish (cyanotic) tint to the skin. But a bluish tint may appear on the skin during activities that require more oxygen (such as crying and feeding).
Examples of acyanotic defects include:
- Ventricular septal defect, or VSD, is the most common CHD. A VSD is a hole between the two lower chambers (ventricles) of the heart. Small VSDs may close on their own. Medium or larger holes can lead to left-to-right shunting, the need for surgery, and possible heart failure.
- Patent ductus arteriosus, or PDA. Before birth, all babies’ hearts have a hole called the ductus arteriosus. This opening between the aorta and the pulmonary artery allows oxygen-rich blood to bypass the baby’s lungs and flow directly to the body while the baby is developing in the womb. When a baby is born and begins breathing on its own, the ductus arteriosus closes, and blood flows to the lungs to pick up oxygen. Typically, the ductus arteriosus closes within a few days after birth. When it does not, it is called a patent (meaning “open”) ductus arteriosus. With a PDA, some oxygen-rich blood travels from the heart to the body, but some also flows back into the lungs instead. A PDA can be caused when a newborn has low blood oxygen levels. Infants born too soon (premature) are more likely to have PDA and often have respiratory issues resulting in low blood oxygen levels. This is one reason why CHD occurs more often in babies who are born early.
- Narrowing (coarctation) of the aorta. This narrowing of the aorta can block or slow blood flow. This makes it harder for the heart to pump blood from its left side into the body. It can cause higher blood pressure in the arms and lower blood pressure in the legs. The extra work and higher pressure can lead to an enlarged left side of the heart. Surgery to widen or bypass the narrow area may be needed.
Cyanotic
Cyanotic heart defects cause a mixing of oxygen-rich and oxygen-deprived blood in the body. In cyanotic defects, blood enters the right side of the heart but leaves the heart before reaching the lungs to get oxygen. This is a problem because all parts of the body — from the brain to the muscles — need oxygen to function. Without enough oxygen-rich blood, the skin, lips, and nails may turn bluish.
Examples of cyanotic defects include:
- Hypoplastic left heart syndrome, or HLHS. The left ventricle is most noticeably smaller or less developed than typical. Other heart structures tend to be less developed as well. This leaves only the right side of the heart (right ventricle) fully functional. If the infant also has other heart defects, such as a VSD or PDA, these defects are left open on purpose to allow better blood flow until surgery to repair HLHS can occur. Surgery for HLHS has three stages; the first occurs when the baby is only a few days old.
- Tetralogy of Fallot, or TOF. This is the most common complex defect. It consists of four problems:
- A VSD.
- A narrowing of the pulmonary valve (the path blood takes to get to the lungs and the muscular area beneath it).
- A thickening of the right ventricle.
- An abnormal position of the aorta that can decrease blood flow to the lungs.
While CHD may occur without any related health conditions, they often occur alongside other conditions or syndromes, including:
- Premature birth.
- Down syndrome.
- DiGeorge syndrome.
- Williams syndrome.
- Fetal alcohol syndrome.
- Other genetic disorders.
Additional complications of CHD may include:
- Heart failure or infections.
- Stroke.
- Heart rhythm problems.
- Limited ability to take part in or enjoy physical activity.
- Increased risk of obesity.
- Behavioral changes.
- Developmental delays.
Signs and Symptoms
Children with CHD may have a variety of symptoms. Symptoms may be related to the size and type of defect. For example, a newborn with a small VSD may not show symptoms of a CHD or be diagnosed until childhood. A newborn with a large defect may have trouble with feeding and gaining weight, which may lead to an earlier diagnosis and possible need for surgery in the first year of life.
Common symptoms of CHD in infants and toddlers include:
- Getting tired during feeding or play.
- Breathing faster or harder than expected.
- Not keeping up with other children.
- Delays in rolling, sitting, crawling, or walking.
- Pale or blueish skin tones, especially around the lips or nail beds.
- Slow or limited weight gain, despite feeding well.
Common symptoms in childhood include:
- Passing out during play.
- Feeling their heart race.
- Feeling chest pain.
- Having trouble breathing when playing.
- Swelling of the hands, ankles, or feet.
- Avoiding active games or sports.
- Needing frequent breaks.
Talk to your pediatrician or cardiologist if your child is having any of these symptoms.
How Is It Diagnosed?
Doctors can find CHDs during pregnancy, soon after birth, in childhood, or even during the teen years. Some heart problems are first seen on a prenatal ultrasound and then checked with an echocardiogram (ECHO). An ECHO is a safe test that uses sound waves to take pictures of the heart.
After birth, most babies have a quick screening using pulse oximetry. This painless assessment checks the baby’s oxygen level and can help find serious heart problems early. Doctors may also use other tests, such as an electrocardiogram (ECG), chest X-ray, or heart MRI, if more information is needed.
Finding CHD early helps the medical team plan care and treatment. This is especially important for babies with cyanotic heart defects.
How Can a Physical Therapist Help?
If your child struggles with movement, tires easily, avoids physical activity, or falls behind on motor milestones, a physical therapist can help improve strength, endurance, and confidence in movement.
After a child is diagnosed with CHD, a physical therapist can work with your child’s medical team to help you better understand your child’s needs. Physical therapists also teach families safe ways to support play, positioning, and daily activities.
A physical therapist will perform an evaluation that includes:
- A thorough review of the medical history, including heart structure, medications, surgeries, as well as any available test results and imaging.
- Discussion of family routines, concerns, and goals.
- Developmental assessment based on the child’s age.
- Muscle strength and flexibility testing.
- Walking or running tests to measure exercise capacity.
- Tests of coordination and balance.
- Monitoring of breathing and heart rate.
With input from you and your child and in partnership with the medical team, your physical therapist will design a treatment plan tailored to your child’s needs and goals. Your physical therapy plan may include:
Education. Your physical therapist will design and teach you how to do a home exercise program. They may recommend lifestyle changes and teach you and your child how to manage their condition. Physical therapists may also explain any concerning signs and symptoms to watch for during rest and activity.
Playtime. Babies with CHD are at risk for developmental delays. Your physical therapist will help caregivers incorporate activities into your infant’s daily routine to support development, including tummy time, rolling, and reaching.
Aerobic exercise. People with CHD are at risk for low exercise tolerance in childhood and adulthood. A physical therapist can design and monitor a personalized exercise program to help increase aerobic endurance. An aerobic exercise program improves physical activity tolerance and quality of life. Physical therapists help children and families explore various forms of aerobic exercise, such as walking, dancing, biking, or playing on a playground. Finding an enjoyable physical activity is important for anyone, especially people with CHDs.
If Surgery Is Needed
Many CHDs require surgery to repair them. A physical therapist may see your child before, after, or between surgeries:
Before surgery, your physical therapist may complete a baseline assessment of development or fitness. They will provide education on movement on post-surgical movement.
After surgery. A physical therapist can:
- Provide education to caregivers on how to safely move and position your child after surgery.
- Advise you on safe playtime and movement after surgery.
- Promote improved breathing patterns and upper body movement.
- Help support your child returning to functional activities.
- Assist with scar healing.
Between surgeries. Some CHDs, such as HLHS, involve a series of staged surgeries. A physical therapist can help support your child’s motor development and endurance as they recover from one surgery and get ready for the next surgery. They will show you how to engage in play activities that help with rib cage development as they grow. This is particularly important if your child had heart surgery that required opening their chest. Physical therapists can also help children reach their walking milestones more quickly and work with them to improve activity tolerance.
Some hospitals offer outpatient pediatric cardiac rehabilitation. Cardiac rehab is a program for people who are recovering from heart disease, heart failure, and heart surgery. Medical professionals, including physical therapists, run this structured program of physical conditioning and lifestyle counseling. Participating in an outpatient pediatric cardiac rehab program has been shown to:
- Increase physical activity, which is important for overall health, especially for people with heart conditions.
- Improve development and cognition.
- Promote healthy lifestyle habits.
- Improve quality of life.
Can This Injury or Condition Be Prevented?
The exact cause of CHDs is unknown. Some reported environmental and genetic factors may increase the risk of CHD:
- Rubella infection during pregnancy.
- Uncontrolled maternal diabetes.
- Smoking or alcohol intake during pregnancy.
- Family history and genetics.
- Medications taken during pregnancy.
Because people with CHD may avoid physical activity and resort to frequent sitting, they are at an increased risk for other health issues, such as obesity. Physical therapists provide important support to establish healthy habits from an early age.
What Kind of Physical Therapist Do I Need?
All physical therapists are trained through education and experience to evaluate, manage, and treat various symptoms and conditions. Families with children who have CHD may want to consider:
- A physical therapist experienced in treating individuals with CHD.
- A physical therapist who is a board-certified clinical specialist in pediatrics, cardiovascular and pulmonary physical therapy, or a physical therapist who has completed a residency or fellowship in pediatrics or cardiovascular and pulmonary physical therapy. These physical therapists may use PCS or CCS after their names on business cards or in their website profiles. Physical therapists with these qualifications have advanced knowledge, experience, and skills to treat children with CHD.
- A physical therapist who has a practice that focuses on pediatrics or cardiovascular and pulmonary physical therapy, including a formal pediatric cardiac rehabilitation program (usually associated with a hospital).
You can find physical therapists near you with specific experience or expertise using the American Physical Therapy Association’s Find a PT tool.
General tips when you're looking for a physical therapist (or other healthcare provider):
- Ask family, friends, or other healthcare providers to recommend a physical therapist.
- Ask about the physical therapist’s experience treating children with congenital heart defects before you make an appointment.
- Be prepared to describe your symptoms in as much detail as possible, including what makes your symptoms worse or better.
The APTA Academy of Pediatric Physical Therapy contributed to this consumer resource. It is for informational purposes only and is not intended to represent the position of APTA Pediatrics.
The American Physical Therapy Association believes consumers should have easy access to clear, reliable information that helps them make informed health care decisions and feel prepared for visits with their providers.
The following resources offer the latest and best scientific evidence on physical therapy for congenital heart defects. They cover recent research and standards of practice in the United States and globally. Whenever possible, they link to PubMed* abstracts (some of which offer free full-text access) or to other resources. You can read them to learn more or share them with your health care provider.
American Heart Association. https://www.heart.org/en/health-topics/congenital-heart-defects. Accessed January 28, 2026.
Centers for Disease Control and Prevention. Congenital heart defects. https://www.cdc.gov/ncbddd/heartdefects/index.html. Accessed January 28, 2026.
Tran D, Maiorana A, Ayer J, et al. Recommendations for exercise in adolescents and adults with congenital heart disease. Prog Cardiovasc Dis. 2020;63(3):350-366. Article Summary on PubMed
Brown TM, Pack QR, Aberegg E, et al. Core components of cardiac rehabilitation programs: 2024 update: A scientific statement from the American Heart Association and the American Association of Cardiovascular and Pulmonary Rehabilitation. Circulation. 2024;150(18):e328-e347. Article Summary on PubMed
*PubMed is a free public website run by the National Library of Medicine. It allows people to access summaries and references from health research articles published in scientific journals, including those indexed in MEDLINE.
Expert Review:
Jun 28, 2026
Revised:
Sep 14, 2026
Content Type: Guide
Congenital Heart Defects
PT, DPT, board-certified clinical specialist in pediatric physical therapy, on behalf of the APTA Academy of Pediatric Physical Therapy
Amanda Clifton
PT, DPT, board-certified clinical specialist in pediatric physical therapy